A referral isn't finished when it's sent.
Between an outgoing request and an understood next step, responsibility changes hands. That is where the process deserves a closer look.
Separate 'sent' from 'complete'
An outgoing referral records one action. It does not by itself tell a practice that the receiving service has accepted the request, that an appointment has happened, or that a response has reached the right person.
AHRQ's Patient Safety Network describes a safer-referral guide that follows the process from ordering a referral through to communicating the resulting plan to patients and families. That broader view is the starting point for this article.
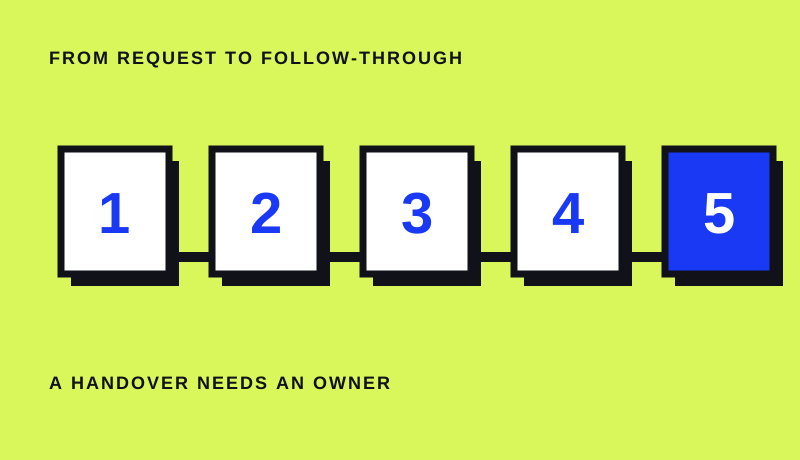
The five-stage map below is our simplified discussion aid. It is not the source guide's full process, a clinical protocol or a substitute for the arrangements in a particular health system.
Draw the journey in five stages
- Request. What was requested, and where is that request recorded?
- Receipt. How does the sending team know the destination received it?
- Arrangement. Who communicates the appointment or other next step?
- Response. Where does the receiving service send its findings?
- Follow-through. Who reviews the response and explains the agreed next action?
For each stage, distinguish the expected event from evidence that it happened. Also mark the point at which the responsible team needs to make a decision. The appropriate timing and urgency are clinical matters; do not turn a generic diagram into a deadline for every referral.
Name the owner of each handover
'The practice follows this up' is a useful intention but an incomplete description. Which role receives the task? Who is the backup? How is unresolved work visible when that person is away?
Use roles rather than individual names when mapping the ordinary process. Then check whether the team agrees on those roles. Different answers reveal a question to resolve, rather than a reason to blame a particular employee.
A shared inbox is a location, not an owner. Likewise, an automatic notification does not establish that a professional has reviewed its contents. Separate receipt, review and action in the map.
Include the paths that do not go to plan
A useful map needs room for a request being returned, an appointment changing, or a patient being unable to use the proposed arrangement. These are not all the same event and should not be hidden under one generic 'pending' label.
Fictional example
A referral reaches a service, but a missing document prevents booking. The request was sent successfully. The next task is still unresolved. Which role receives that information and tells the patient what happens next?
Discuss the exception process with the people who handle it. Keep actual patient information inside the approved clinical systems; an editorial worksheet is not a place to store it.
Use the map to ask better questions
The point of the exercise is to locate uncertainty. Where does work wait? Which status descriptions mean different things to different people? Can a new colleague tell who takes over when the usual owner is unavailable?
Before calling a change successful, decide what would demonstrate a better process in that setting. A larger number of messages sent may reflect more activity without showing a completed journey. Review the full process rather than selecting the easiest number to count.
Our onboarding guide includes a fictional referral exercise for new colleagues. For the patient's view of the next action, see clear patient communication.
Sources & further reading
- AHRQ PSNet · Closing the Loop: safer ambulatory referrals
- AHRQ PSNet · Patient safety in the ambulatory care setting
Sources checked 30 September 2026. The examples and discussion exercises in this article are original editorial illustrations.